Data Analysis services

Meta-Analysis Research Services

Data Collection Services

Statistical Programming & Biostatistics services

Data Management Services

Research methodology services

Tool development services
Statistical Interpretation services

Statistical Interpretation services
Sample Size Calculation Services

Sample Size Calculation Services
Artificial Intelligence and Machine Learning Services

Artificial Intelligence and Machine Learning Services
Report generation Service

Report generation Services
Surgeon experience can influence operating time, complications, conversion rates and resource use during medical device adoption. A meta-analysis that combines early adoption cases with established practice without accounting for learning may produce estimates that are poorly suited to clinical and economic decision-making.
For Swiss health technology assessment (HTA), learning-related uncertainty can affect assessments of healthcare services and procedures involving medical technologies. Appropriate analysis requires systematic extraction of experience-related outcomes, selection of defensible statistical models, validation of learning-curve estimates and transparent economic evaluation.
Article 32 of Switzerland’s Federal Health Insurance Act (KVG/LAMal) establishes effectiveness, appropriateness and economic efficiency as criteria for reimbursed benefits. The Federal Office of Public Health (FOPH/BAG) HTA programme evaluates healthcare services and interventions; it should not be interpreted as a universal device-specific assessment pathway. [1,2]
Early procedures may take longer and involve more technical difficulties than procedures performed after experience accumulates. However, learning varies by surgeon, procedure, device, outcome and clinical setting.
Ignoring experience may produce pooled estimates that represent neither initial adoption nor established practice. Expert-centre studies may overstate performance achievable during wider implementation, while studies dominated by early cases may overstate risks during mature use.
The appropriate analysis depends on the decision question, comparator and intended implementation setting. The objective is to estimate clinically relevant performance while distinguishing learning-related variation from patient characteristics, centre expertise and other sources of heterogeneity.
The review protocol should prespecify how surgeon experience and chronological outcomes will be identified. PRISMA 2020 supports transparent reporting of systematic reviews but does not prescribe a specific learning-curve model. [3]
Searches should combine device and procedure terms with phrases such as learning curve, cumulative case volume, surgeon experience, operator proficiency and training.
Extract, where available:
Experience phases from the same surgeon or centre are not necessarily independent. Treating repeated phases as independent observations can underestimate uncertainty. The IDEAL framework can inform systematic evaluation and reporting of surgical innovation, although it does not prescribe one universal statistical model. [7]
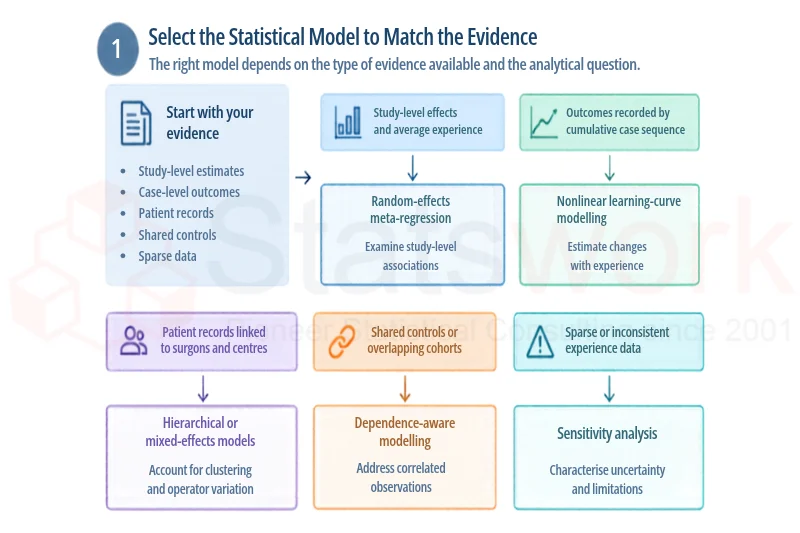
Evidence available | Analytical approach | Primary purpose |
Study-level effects and average experience | Random-effects meta-regression | Examine study-level associations |
Outcomes recorded by cumulative case sequence | Nonlinear learning-curve modelling | Estimate changes with experience |
Patient records linked to surgeons and centres | Hierarchical or mixed-effects models | Account for clustering and operator variation |
Shared controls or overlapping cohorts | Dependence-aware modelling | Address correlated observations |
Sparse or inconsistent experience data | Sensitivity analysis | Characterise uncertainty and limitations |
When studies report comparable effect estimates and experience measures, random-effects meta-regression can investigate whether study-level experience is associated with treatment effects.
A standard model is:
y_i=θ_i+ε_i
θ_i=β_0+β_1 X_i+u_i
Here, is the observed effect estimate, is the underlying study effect, is a prespecified study-level experience measure, and represents its association with the underlying effect. The residual between-study variation is represented by , conventionally modelled with variance , while represents sampling error.
The model assumes an appropriate sampling-error structure. Multiple estimates from shared controls or overlapping cohorts may require covariance modelling.
Importantly, does not estimate the causal effect of an individual surgeon gaining experience. Study-level associations may be confounded by patient selection, training, centre expertise and device generation. Meta-regression also requires sufficient studies and meaningful variation in experience. The commonly cited heuristic of approximately ten studies per covariate is not a universal minimum or guarantee of adequate power. [5,6]
When outcomes are recorded by cumulative procedure sequence, an exponential model may be considered:
Here, is the expected outcome after procedures, is the initial expected outcome, is the asymptotic plateau, and determines the rate of change.
This is an illustrative model, not a universal form. Restricted cubic splines or piecewise models may better represent gradual, abrupt or non-monotonic changes when sufficient observations are available. Operating time and complication risk may also follow different learning trajectories. [4,8]
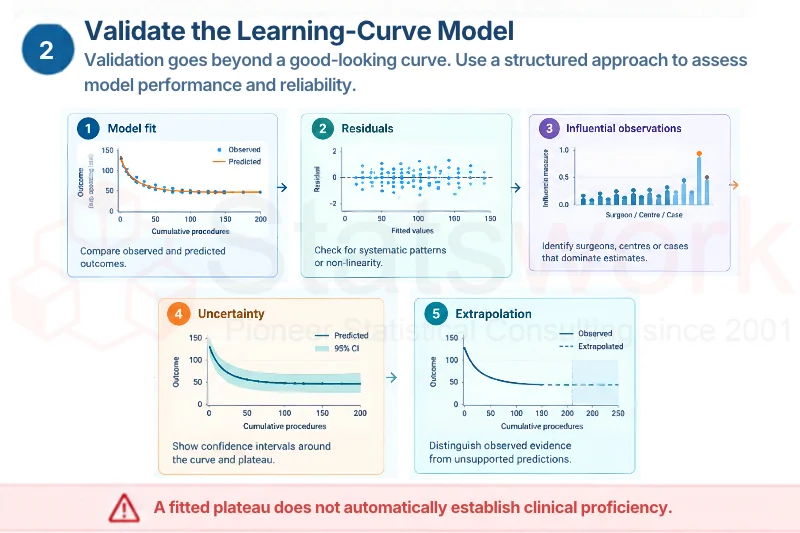
Model selection should be followed by explicit validation rather than relying solely on a good-looking fitted curve.

Image 2: validating the learning-curve model
A fitted plateau is not automatically evidence of clinical proficiency. The plateau and any proficiency threshold should be clinically meaningful, supported by adequate data and interpreted alongside uncertainty. Internal validation or cross-validation may help assess predictive performance when the dataset is sufficiently large, but neither can compensate for sparse or unrepresentative evidence.
Surgical studies may include repeated experience phases, several surgeons within one centre, shared control groups or overlapping patient cohorts. Treating correlated observations as independent can underestimate standard errors and produce overly narrow confidence intervals.
Map surgeons, centres, recruitment periods, comparators and cohorts before pooling results. Consider multilevel models for clustered observations, appropriate covariance structures for shared controls, and a defensible non-overlapping dataset when cohort overlap cannot be resolved.
Robust variance estimation may be useful in some settings, but its reliability depends on the assumptions and number of independent clusters. Adding a random-effects term alone does not necessarily resolve every form of dependence.
Consider a hypothetical scenario, not observed Swiss clinical evidence.
| Outcome | Early cases | Established cases |
| Mean operating time | 150 minutes | 100 minutes |
| Complication rate | 12% | 6% |
| Conversion rate | 8% | 4% |
Suppose 100 procedures comprise 40 early cases and 60 established cases. The weighted mean operating time is:
T ̅=(40(150)+60(100))/100=120″ minutes”
Expected complications equal , while expected conversions equal . These are expected values, not fractional actual patients.
Assume illustrative costs of CHF 30 per operating-room minute, CHF 4,000 per complication and CHF 2,500 per conversion. Under additive-cost assumptions with no overlap between event costs, the results are:
| Cost component | Mixed adoption | Established performance for all cases |
| Operating-room time | CHF 360,000 | CHF 300,000 |
| Complications | CHF 33,600 | CHF 24,000 |
| Conversions | CHF 14,000 | CHF 10,000 |
| Total per 100 procedures | CHF 407,600 | CHF 334,000 |
The difference is CHF 73,600 per 100 procedures under these assumptions. This is an illustrative cost comparison, not an empirical Swiss estimate or proof of causality. Actual analyses should account for uncertainty, clustering, overlapping events and possible double counting.
The example above estimates costs under alternative adoption scenarios. It resembles a simplified budget-impact calculation because it focuses on the financial consequences of different patterns of implementation. A budget-impact analysis typically estimates the expected financial consequences for a defined payer or healthcare budget over a specified period, accounting for eligible population size, uptake and relevant costs.
A cost-effectiveness analysis asks a different question: how do costs and health outcomes compare between an intervention and its comparator?
Incremental costs are calculated as:
ΔC=C_”device” -C_”comparator”
Incremental health outcomes are:
ΔE=E_”device” -E_”comparator”
When appropriate, the incremental cost-effectiveness ratio (ICER) is:
ICER=ΔC/ΔE
The health outcome might be quality-adjusted life-years (QALYs), complications avoided or another prespecified outcome. The choice should match the decision context and relevant evaluation requirements. An ICER must be interpreted alongside uncertainty and the direction of incremental costs and effects; it is not meaningful in every decision scenario.
For Swiss HTA, learning-adjusted estimates may inform operating costs, complications, training requirements and health outcomes in an economic model. Probabilistic sensitivity analysis, alternative adoption scenarios and structural sensitivity analyses can test how uncertainty in the learning curve affects conclusions.
Use appropriate Swiss-specific costs and the relevant analytical perspective. Avoid double-counting costs when operating time, complications and conversions overlap. If the learning curve is weakly identified, test plausible alternatives rather than presenting an uncertain plateau as established fact.
Statswork’s Meta-Analysis services help you combine surgical evidence, model learning curves, identify sources of heterogeneity and quantify uncertainty in clinical outcomes and adoption costs. Preparing a medical-device evaluation for Swiss HTA? Contact Statswork today to discuss your dataset and receive tailored statistical support for a robust, reproducible analysis that strengthens your evidence-based decisions.
Surgeon learning curves should be considered during review design, statistical modelling and economic evaluation. Meta-regression examines study-level associations, while direct learning-curve models estimate changes with cumulative experience. IPD and hierarchical models can provide additional insight when suitable data are available.
Model validation should assess fit, residual patterns, influential observations, parameter uncertainty and the credibility of estimated plateaus. Economic evaluations should distinguish budget impact from cost-effectiveness and carry relevant clinical uncertainty into estimates of incremental costs and health outcomes.
Experience may influence operating time, complications and conversions, affecting pooled clinical estimates and resource-use assumptions.
Not automatically. Learning must be explicitly investigated through an appropriate model or analysis.
Assess model fit, residual patterns, influential observations, parameter uncertainty, plateau identifiability and robustness to alternative specifications.
No. It estimates study-level associations that may be confounded by other study characteristics.
Budget impact estimates financial consequences for a defined budget and period. Cost-effectiveness compares incremental costs with incremental health outcomes, potentially using an ICER.
WhatsApp us